Stabilize
- ABCs, vitals, seizure onset time
- IV access, ECG, finger-stick glucose
- Treat hypoglycemia immediately with IV dextrose (or IM glucagon if no IV). Give thiamine before or with glucose when deficiency is suspected; never delay glucose.
NeuroLogic: Seizure Management
Choose a topic to review the relevant pathway and reference material. Doses and treatment decisions should be checked against the local protocol and current prescribing information.
Adult emergency pathway: treat ongoing convulsions at 5 minutes, or recurrent convulsions without recovery. Include treatment already given before arrival.
Use this as the emergency entry point: stabilize, give benzodiazepine therapy early, load a second-line ASM if convulsions continue, and escalate promptly if adequately dosed initial treatments fail. The time ranges below are targets, not waiting periods.
t₁ = 5 minutes: treat now. t₂ = 30 minutes: lasting injury becomes likely. Refractory status begins when a benzodiazepine and one second-line ASM fail.
After the movements stop: persistent impaired consciousness can reflect ongoing nonconvulsive seizures. Arrange urgent EEG when the patient does not return toward baseline. The anesthetic pathway above addresses refractory convulsive status; other electrographic patterns require clinical interpretation.
Doses and treatment sequence: ENLS status epilepticus protocol and ESETT trial. Reviewed September 2026; use the local emergency protocol for administration and monitoring.
Courtesy of Dr. Gena Ghearing
The “five minute rule” is not a rule about seizures in general — it is t1 for convulsive status only. The ILAE 2015 operational definition sets two separate clocks, and they differ by seizure type:
| Type of status epilepticus | t1 — treat now | t2 — risk of lasting injury |
|---|---|---|
| Tonic–clonic (convulsive) | 5 minutes | 30 minutes |
| Focal with impaired consciousness | 10 minutes | > 60 minutes |
| Absence status | 10–15 minutes | Unknown |
Use the clocks correctly: these operational estimates vary by seizure type and do not establish a safe waiting period. Clinical deterioration, recurrent seizures without recovery, or uncertain onset requires prompt assessment and treatment. The time associated with injury is less certain in nonconvulsive status.
Trinka E, Cock H, Hesdorffer D, et al. A definition and classification of status epilepticus — Report of the ILAE Task Force on Classification of Status Epilepticus. Epilepsia 2015;56(10):1515–23.
| Phase | Time Range | Intervention & Dosing |
|---|---|---|
| Stabilization Phase | 0–5 minutes |
|
| Initial Therapy Phase | 5–10 minutes |
|
| Second-line Therapy | 10–30 minutes |
|
| Refractory Therapy | After adequate benzodiazepine + second-line ASM fail; do not wait for 30 minutes |
|
| Breakthrough/Recurrence | N/A |
|
| Additional Therapies | N/A |
|
Search by medication, mechanism, dosing, side effect, or level.
Sodium channel
Slow sodium inactivation
Calcium channel
GABA enhancement
SV2A binding
AMPA antagonist
Multiple or other
Disease-specific
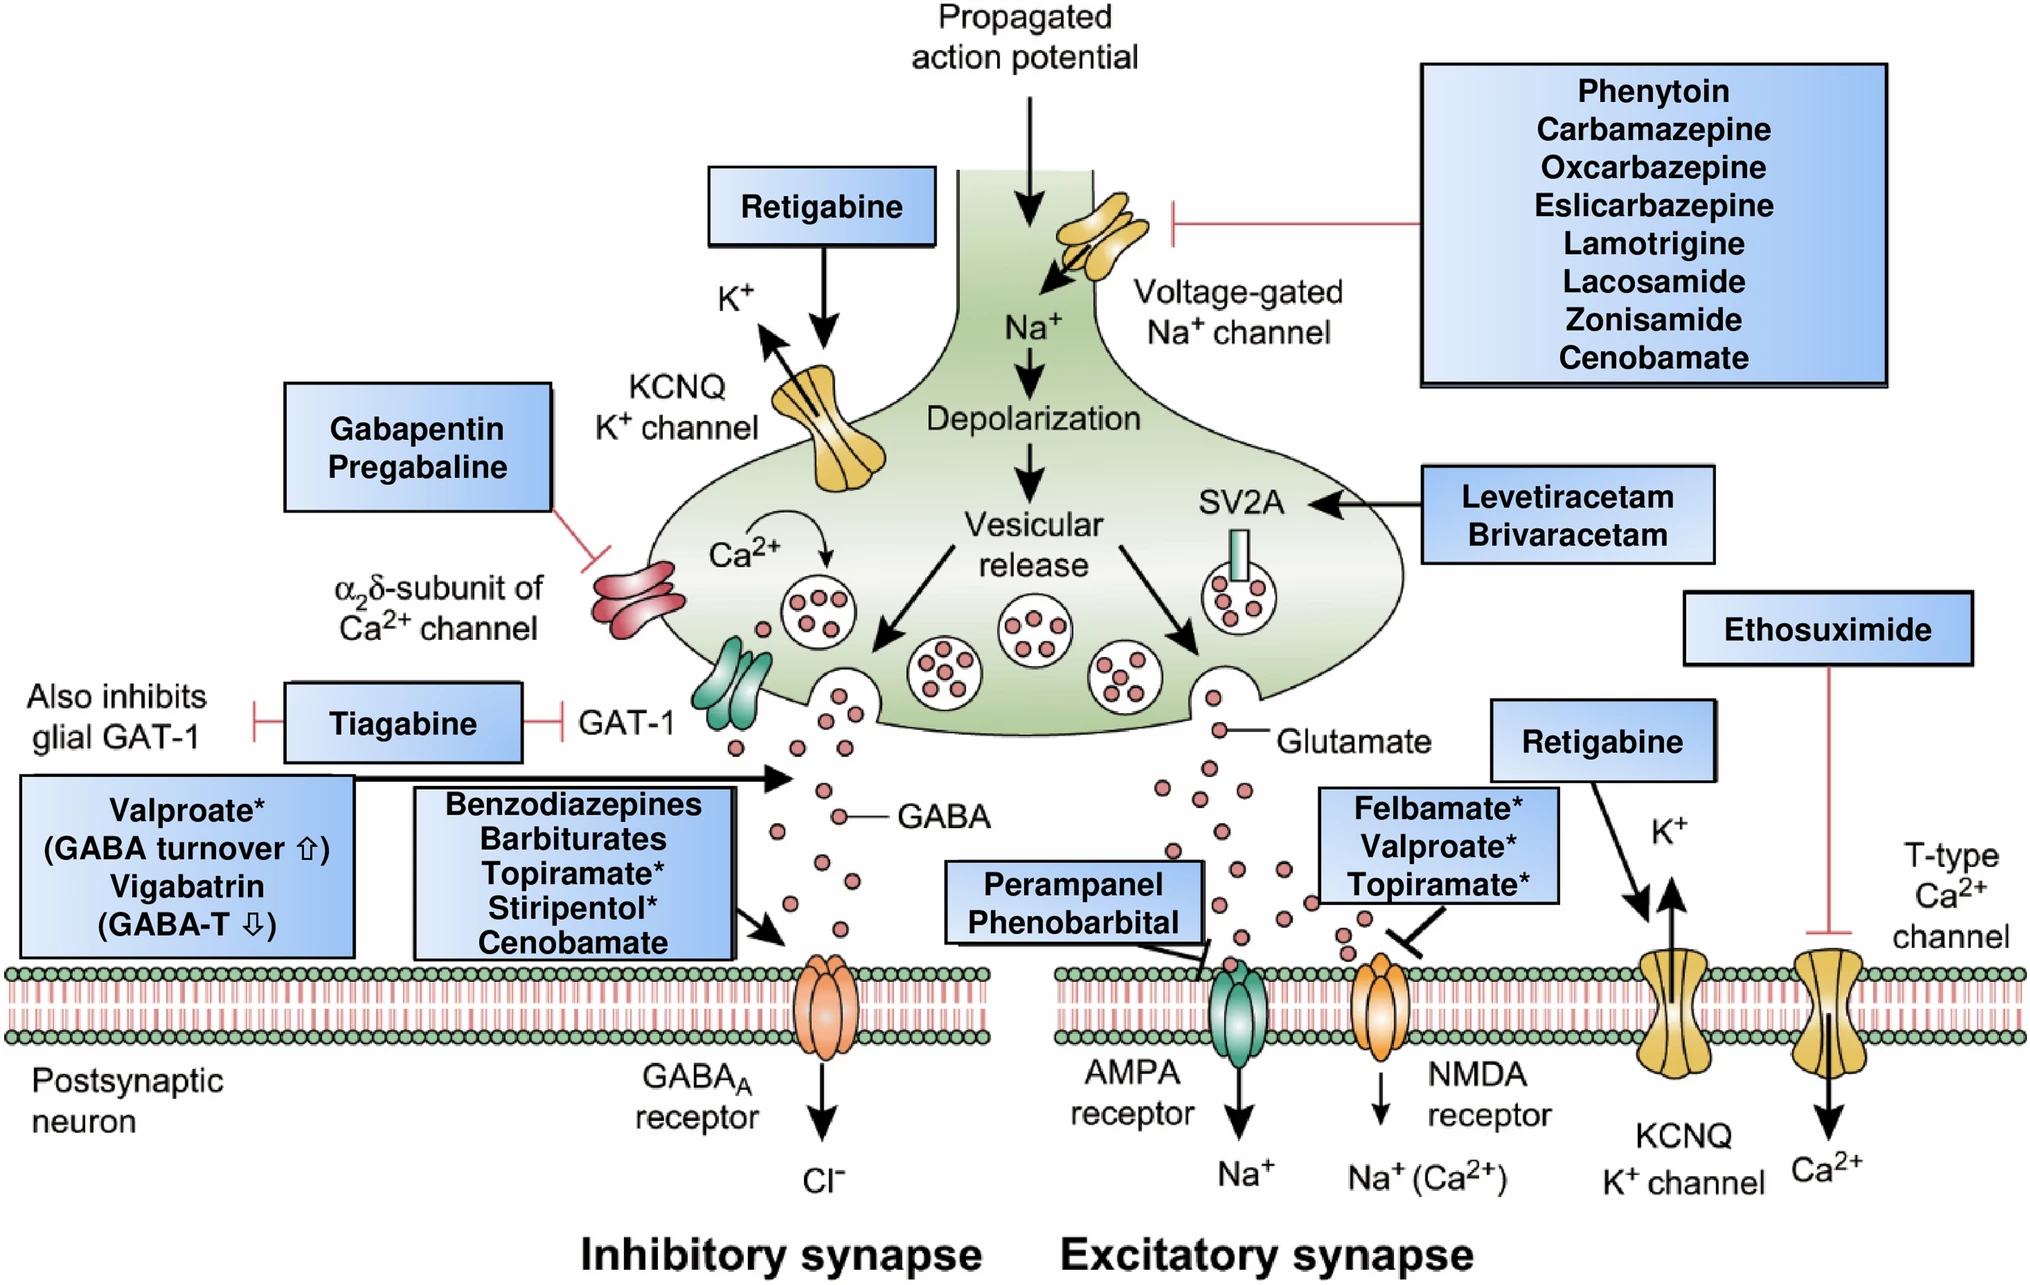
Each drug is listed by its main mechanism; several act in more than one way. Board Review has an interactive map of where each drug acts.
This rapid reference includes abbreviated adult epilepsy dosing, common adverse effects, and laboratory intervals when applicable. Some entries are syndrome-specific, adjunctive, rescue, or off-label uses rather than interchangeable maintenance regimens.
| Medication | Mechanism / Target | Abbreviated Adult Epilepsy Dosing | Common Side Effects | Common Laboratory Reference Range* |
|---|---|---|---|---|
| Acetazolamide | Carbonic anhydrase inhibitor | Oral: 375–1000 mg/day (divided doses) | Paresthesias, fatigue, taste alteration, acidosis, kidney stones | N/A |
| Brivaracetam | SV2A ligand — higher affinity and more selective than levetiracetam | Oral or IV: 50–200 mg/day (in 2 divided doses) | Drowsiness, dizziness, fatigue, irritability | N/A |
| Carbamazepine | Sodium channel blockade (fast inactivation) | Oral: 800–1200 mg/day (in 2–4 divided doses; range ~400–1600 mg) | Dizziness, drowsiness, diplopia, ataxia, hyponatremia, leukopenia; serious rash including SJS/TEN (HLA-B*15:02 screening recommended before initiation for patients with ancestry in populations where HLA-B*15:02 is common; consider HLA-A*31:01 risk according to ancestry and local guidance) | 4–12 µg/mL |
| Cannabidiol (Dravet, LGS, or TSC-associated seizures) | Not fully defined — GPR55 antagonism, TRPV1 desensitisation, adenosine reuptake inhibition. Not a CB1 agonist | Oral: target 10 mg/kg/day for Dravet/LGS (maximum 20 mg/kg/day); target 25 mg/kg/day for TSC, divided BID | Diarrhea, fatigue, decreased appetite, somnolence; raised transaminases, especially with valproate (check liver tests before and during treatment) | N/A |
| Cenobamate | Dual: inhibits the persistent sodium current and positively modulates GABA-A at a non-benzodiazepine site | Oral: 200 mg/day (after gradual titration; max 400 mg/day) | Dizziness, somnolence, fatigue, headache, nausea; DRESS with fast titration; shortens the QT interval (contraindicated in familial short-QT syndrome) | No established therapeutic target |
| Clobazam (adjunct for LGS) | 1,5-benzodiazepine — positive allosteric GABA-A modulator (the other benzodiazepines used for seizures are 1,4-benzodiazepines) | Oral: 10–40 mg/day (usually divided BID) | Sedation, drowsiness, drooling | Clobazam 30–300 ng/mL; N-desmethylclobazam 300–3000 ng/mL |
| Clorazepate | Benzodiazepine prodrug → nordiazepam; positive allosteric GABA-A modulator | Oral: 15–90 mg/day (divided doses) | Drowsiness, dizziness, fatigue, ataxia | N/A |
| Clonazepam (rarely used long-term) | Benzodiazepine — positive allosteric GABA-A modulator | Initial dose should not exceed 1.5 mg/day divided TID; titrate individually. Labeled maximum 20 mg/day. | Sedation, drowsiness, cognitive impairment, tolerance | N/A |
| Diazepam | Benzodiazepine — positive allosteric GABA-A modulator | Oral: 4–40 mg/day (divided doses). IV or IM for status epilepticus (labeled adjunct): 5–10 mg, IV preferred, repeated at 10–15 minute intervals to a maximum of 30 mg (the protocol above uses 0.15–0.2 mg/kg, maximum 10 mg). Rectal gel or nasal spray (Valtoco) for seizure clusters: 0.2 mg/kg at 12 years and older (0.3 mg/kg at 6–11 years, 0.5 mg/kg at 2–5 years), rounded to the unit dose; a second dose may follow 4–12 hours later. | Sedation, fatigue, ataxia, muscle weakness; venous thrombosis and phlebitis at the IV injection site; somnolence after the rectal gel | N/A |
| Eslicarbazepine acetate | Prodrug → eslicarbazepine; sodium channel blockade, stabilizing the inactivated state | Oral: 800–1600 mg/day (usually once daily) | Dizziness, headache, diplopia, somnolence | N/A |
| Ethosuximide | T-type calcium channel blockade in thalamocortical relay neurons | Oral: start 500 mg/day and titrate; doses above 1500 mg/day require strict medical supervision (absence seizures) | Nausea, vomiting, lethargy, headache, weight loss | 40–100 µg/mL |
| Everolimus (TSC associated seizures) | mTOR inhibitor — targets the pathway disrupted in tuberous sclerosis | Oral: Titrated to trough 5–15 ng/mL | Stomatitis, infections, rash, fatigue | 5–15 ng/mL |
| Felbamate (rarely used – toxicity) | NMDA receptor blockade (channel block, favoring GluN2B-containing receptors), plus sodium channel blockade and GABA-A potentiation | Oral: 1200–3600 mg/day (divided TID–QID) | Sedation, nausea, vomiting, risk of aplastic anemia/liver failure | N/A |
| Fenfluramine | Serotonin release and 5-HT receptor agonism (notably 5-HT2C), with sigma-1 receptor modulation | Oral solution: 0.1 mg/kg BID initially; up to 0.35 mg/kg BID (maximum 26 mg/day). Lower maximum with stiripentol plus clobazam. | Decreased appetite, somnolence, diarrhea, fatigue; boxed warning requires echocardiographic monitoring for valvular heart disease and pulmonary arterial hypertension | No established therapeutic target |
| Fosphenytoin (parenteral only) | Water-soluble prodrug of phenytoin; voltage-dependent sodium channel blockade. Dosed in phenytoin sodium equivalents (PE): 1.5 mg fosphenytoin = 1 mg PE | IV for generalized tonic–clonic status epilepticus: loading 15–20 mg PE/kg at 100–150 mg PE/min. Non-emergent loading: 10–20 mg PE/kg IV or IM; maintenance 4–6 mg PE/kg/day in divided doses. Also labeled for seizures during neurosurgery and as a short-term substitute for oral phenytoin. Infusion must not exceed 150 mg PE/min (boxed warning). | Pruritus, nystagmus, dizziness, somnolence, ataxia; hypotension and cardiac arrhythmias with rapid infusion (cardiac monitoring during and after the infusion) | As phenytoin: total 10–20 µg/mL, unbound 1–2 µg/mL; do not measure until conversion is complete (about 2 h after an IV infusion, 4 h after IM) |
| Gabapentin (adjunctive therapy for focal seizures) | Binds the alpha-2-delta subunit of voltage-gated calcium channels. Despite the name, not a GABA agonist | Oral: 900–3600 mg/day (divided TID) | Dizziness, somnolence, peripheral edema, ataxia | N/A |
| Ganaxolone (CDKL5 deficiency) | Neuroactive steroid — positive allosteric modulator of synaptic and extrasynaptic GABA-A receptors | Oral: Titrated to 600 mg TID (1800 mg/day) | Somnolence, pyrexia, salivary hypersecretion | N/A |
| Lacosamide | Enhances slow inactivation of sodium channels — a different action from the classic fast-inactivation blockers | Oral or IV: 200–400 mg/day divided BID; 600 mg/day was not more effective and caused more adverse reactions in trials | Dizziness, headache, nausea, diplopia; PR prolongation and AV block (ECG when there is cardiac disease or other PR-prolonging drugs) | 10–20 µg/mL |
| Lamotrigine | Sodium channel blockade with inhibition of glutamate release | Oral: 100–400 mg/day in 2 divided doses, reached by slow titration. Valproate roughly halves the dose needed and enzyme inducers raise it, so use the matching titration schedule. | Rash, including Stevens–Johnson syndrome (more likely with fast titration or valproate), dizziness, diplopia, headache | 3–15 µg/mL |
| Levetiracetam | Binds synaptic vesicle protein SV2A, modulating neurotransmitter release | Oral or IV: 1000–3000 mg/day divided BID; adjust for renal function | Drowsiness, dizziness, irritability, behavioral changes | 10–40 µg/mL |
| Lorazepam | Benzodiazepine — positive allosteric GABA-A modulator; no active metabolite | Oral: 2–6 mg/day (divided doses). IV for status epilepticus (labeled): 4 mg slowly at 2 mg/min; one further 4 mg dose after 10–15 minutes if seizures continue (the protocol above uses 0.1 mg/kg, maximum 4 mg). The injection is also labeled for IM use. | Sedation, dizziness, weakness, unsteadiness; with the injection, CNS and respiratory depression | N/A |
| Methsuximide | Succinimide — T-type calcium channel blockade | Oral: 300–1200 mg/day | Nausea, vomiting, dizziness, drowsiness | 10–40 µg/mL (as N-desmethylmethsuximide) |
| Midazolam | Benzodiazepine — positive allosteric GABA-A modulator; short acting | Nasal spray (Nayzilam) for seizure clusters, 12 years and older: 5 mg into one nostril; one further 5 mg into the other nostril after 10 minutes if there is no response (maximum 2 doses per cluster). IV or IM injection: labeled for sedation; the 10 mg IM dose for status epilepticus in the protocol above follows the AES 2016 guideline (RAMPART trial) rather than the label. | Somnolence, headache, nasal discomfort, throat irritation, rhinorrhea; with the injection, respiratory depression and apnea | N/A |
| Oxcarbazepine | Prodrug → licarbazepine (MHD); sodium channel blockade | Oral: 600–2400 mg/day (divided BID) | Dizziness, sedation, hyponatremia | 3–35 µg/mL (MHD) |
| Perampanel | Selective non-competitive AMPA receptor antagonist | Oral: 8–12 mg/day (once daily at bedtime) | Dizziness, somnolence, hostility, irritability, falls | No established therapeutic target |
| Phenobarbital | Barbiturate — prolongs GABA-A chloride channel opening; inhibits glutamate responses at higher concentrations | Oral or IV: 60–200 mg/day (usually once at bedtime) | Sedation, cognitive impairment, ataxia, dependence | 10–40 µg/mL |
| Phenytoin | Use- and voltage-dependent sodium channel blockade (fast inactivation) | Oral or IV: 300–400 mg/day (divided BID; ~5–7 mg/kg/day to maintain level 10–20 µg/mL) | Nystagmus, ataxia, gingival hyperplasia, hirsutism, sedation | Total 10–20 µg/mL; free concentration is often more informative with low albumin, renal failure, pregnancy, or interacting drugs |
| Primidone (rarely used) | Metabolised to phenobarbital and PEMA, both active; GABA-A modulation | Oral: 750–1500 mg/day (divided BID–TID) | Sedation, ataxia, nausea, dizziness | N/A |
| Pregabalin (adjunctive therapy for focal seizures) | Binds the alpha-2-delta subunit of voltage-gated calcium channels | Oral: 150–600 mg/day (divided BID) | Dizziness, somnolence, weight gain, peripheral edema | N/A |
| Rufinamide (rare, LGS) | Prolongs the inactivated state of sodium channels | Oral with food: start 400–800 mg/day divided BID; titrate to a maximum of 3200 mg/day | Dizziness, fatigue, nausea, vomiting | N/A |
| Stiripentol (rare, Dravet) | Positive allosteric GABA-A modulator; also inhibits CYP, raising clobazam and norclobazam levels | Oral: 50 mg/kg/day divided BID or TID (maximum 3000 mg/day), used with clobazam for Dravet syndrome in the labeled population | Drowsiness, ataxia, loss of appetite | N/A |
| Tiagabine (rarely used) | Blocks the GAT-1 GABA reuptake transporter | Oral: 32–56 mg/day (divided BID–QID) | Dizziness, nervousness, fatigue, tremor | N/A |
| Topiramate | Multiple: sodium channels, GABA-A potentiation, AMPA/kainate antagonism, carbonic anhydrase inhibition | Oral: 100–400 mg/day (divided BID) | Cognitive slowing and word-finding difficulty, weight loss, paresthesias, kidney stones, metabolic acidosis; rarely acute angle-closure glaucoma | 5–20 µg/mL |
| Valproate / Divalproex Sodium | Broad and not fully established: sodium channels, increased GABA turnover, histone deacetylase inhibition (no T-type calcium effect in thalamic neurons) | Oral (DR/ER) or IV: 1000–3000 mg/day (divided BID–TID; ~15–60 mg/kg/day) | GI upset, tremor, weight gain, hair loss, hepatotoxicity, thrombocytopenia, hyperammonemia, pancreatitis; the most teratogenic ASM (see Pregnancy) | 50–125 µg/mL |
| Vigabatrin (restricted use; REMS) | Irreversible GABA-transaminase inhibitor, raising brain GABA | For refractory focal seizures: start 1000 mg/day divided BID; titrate to recommended 3000 mg/day | Permanent visual field loss (boxed warning; vision monitoring under the REMS), sedation, irritability | N/A |
| Zonisamide | Sodium channels and T-type calcium channels, with weak carbonic anhydrase inhibition | Oral: 100–400 mg/day (once daily or divided BID) | Dizziness, somnolence, loss of appetite, weight loss | 10–40 µg/mL |

*Laboratory ranges vary by assay and are not universal treatment targets. Clinical response, toxicity, sample timing, baseline concentration, interactions, protein binding, and free drug levels may matter more than a population interval. Doses are abbreviated educational examples; verify whether each use is labeled, adjunctive, syndrome-specific, or off-label.
Medication table for rapid educational reference only. Verify indication, formulation, interactions, organ-function adjustments, pregnancy considerations, titration, and current prescribing information before use.
These flow charts provide guidance on anti-seizure medication selection based on seizure type, mechanisms of action, and clinical applications:
Context: These 2021 figures are conceptual teaching aids, not current prescribing algorithms. Medication approval, pregnancy guidance, syndrome terminology, and comparative evidence change; verify the current label and guideline for the individual patient.
Monotherapy and add-on therapy options for seizures in adults and children:
Neurobiological targets of commonly used anti-seizure medications:
Treatment approaches for different types of epilepsy in adults and children:
Reference: Löscher, W., Klein, P. The Pharmacology and Clinical Efficacy of Antiseizure Medications: From Bromide Salts to Cenobamate and Beyond. CNS Drugs 35, 935–963 (2021). https://link.springer.com/article/10.1007/s40263-021-00827-8
ASM withdrawal should be performed gradually under medical supervision after careful consideration of seizure recurrence risk factors.
Use the prediction tool below to estimate seizure recurrence risk after medication withdrawal, but always consult your epilepsy specialist before making any medication changes.
The aim is to find the epileptogenic zone, the cortex whose removal or disconnection stops the seizures, and to map the function around it. No test shows it directly. Each test defines a different zone, the team infers the epileptogenic zone from where they overlap, and it is only proven when the patient is seizure-free after surgery (Rosenow & Lüders 2001).
| Zone | What it is | Main test |
|---|---|---|
| Seizure-onset zone | Where recorded seizures begin | Ictal scalp or intracranial EEG |
| Irritative zone | Where interictal spikes arise; often larger than the onset zone | EEG, MEG |
| Symptomatogenic zone | Cortex that produces the first symptoms; it can lie away from the onset | Video of the seizures (semiology) |
| Epileptogenic lesion | The structural abnormality | Epilepsy-protocol MRI |
| Functional deficit zone | Cortex that works abnormally between seizures | Examination, neuropsychology, FDG-PET |
| Eloquent cortex | Cortex that must be spared, such as language and motor areas | Functional MRI, Wada test, electrical stimulation mapping |
When the noninvasive results disagree, show no lesion, suggest a deep or bilateral onset, or point to cortex near language or motor areas, the team states a hypothesis about where seizures start and how they spread, and tests it with depth electrodes. Each lead passes through a small drill hole along a trajectory planned on MRI and vascular imaging to avoid vessels, and is placed with a stereotactic frame or robot. About a dozen leads is typical: 902 electrodes in 76 implantations in one series (van der Loo 2017).
Explore implants in 3D in the Epilepsy Brain Atlas. Each example opens with its leads and contacts on a template brain.
| Therapy Category | Description/Details |
|---|---|
| Definition | Drug-resistant epilepsy (DRE) is defined by failure of two tolerated, appropriately chosen and adequately used ASM schedules—whether alone or in combination—to achieve sustained seizure freedom. Referral to a comprehensive epilepsy center should occur promptly so the diagnosis, adherence barriers, epilepsy type, imaging, surgical candidacy, devices, dietary therapy, and psychosocial needs can be reviewed; referral does not commit a patient to surgery. |
| Surgical Options | Resection (lesionectomy, lobar or multilobar resection, hemispherectomy in catastrophic cases) or MRI-guided laser interstitial thermal therapy for a well-localized onset; corpus callosotomy may reduce drop attacks. In the randomized trial of temporal lobe surgery (patients aged 16 and older), 58% were free of seizures impairing awareness at 1 year, against 8% who continued medication (Wiebe 2001). |
| Neuromodulation Techniques |
VNS (FDA 1997; since 2017 labeled for focal seizures from age 4, and also used off label for generalized epilepsies such as Lennox–Gastaut syndrome): mean seizure frequency fell 28% with high stimulation vs 15% with low stimulation at 3 months (Handforth 1998). In a registry of 5,554 patients, responders (at least 50% fewer seizures) rose from 49% at 0–4 months to 63% at 24–48 months, and about 8% became seizure-free (Englot 2016).
RNS (FDA 2013; adults with one or two seizure foci): mean seizure frequency fell 37.9% vs 17.3% with sham in the 12-week blinded period (Morrell 2011). In open-label follow-up the median reduction was 75% at 9 years, and 18% had at least one year free of seizures (Nair 2020). DBS (FDA 2018; adults whose focal seizures have failed three or more ASMs): bilateral stimulation of the anterior nucleus of the thalamus gave a median 40.4% reduction vs 14.5% with sham at the end of the blinded phase (Fisher 2010). Open-label median reductions were 41% at 1 year and 69% at 5 years (Salanova 2015), and 75% at 7 years (Salanova 2021). All three are palliative: the benefit grows over years and seizure freedom is uncommon. Diathermy is contraindicated with each device, and MRI is possible only under the manufacturer's conditions for the implanted system. |
| Dietary & Other Therapies | Ketogenic diet, or a less restrictive version such as the modified Atkins diet or low glycemic index treatment, in children and adults; it is the treatment of choice for GLUT1 deficiency and pyruvate dehydrogenase deficiency. Syndrome-specific medications: cannabidiol (Lennox–Gastaut, Dravet, tuberous sclerosis), fenfluramine (Dravet, Lennox–Gastaut), stiripentol (Dravet), everolimus (tuberous sclerosis) and ganaxolone (CDKL5 deficiency). Immunotherapy when an autoimmune cause is suspected, and clinical trials. |
| References | Definition: ILAE task force (Kwan 2010). VNS: AAN guideline update (Morris 2013). Device indications from the FDA approvals and the manufacturers' labeling; trial results as linked above. |
Sex hormones and antiseizure medications act on each other in both directions, and the questions change across a lifetime: the menstrual cycle, contraception, planning and carrying a pregnancy, breastfeeding, gender-affirming hormones and menopause. Most people with epilepsy who plan a pregnancy have a healthy one. Do not stop an antiseizure medication abruptly because of pregnancy.
Most of the evidence comes from cisgender women, so this topic says “women”. The same principles apply to anyone who menstruates, can become pregnant or takes sex hormones, including transgender and nonbinary people.
Estrogen tends to excite neurons and progesterone to calm them, through its metabolite allopregnanolone at the GABA-A receptor. Seizures cluster when estrogen is high relative to progesterone. Separately, many ASMs change hormone levels, and hormones change ASM levels.
Catamenial epilepsy is a cyclical worsening of seizures tied to the menstrual cycle. Herzog's working definition is a twofold or greater rise in the average daily seizure frequency in one phase of the cycle (Herzog 1997). In 87 women with focal epilepsy who charted three cycles, 39% met it in at least two of the three (Herzog 2004).
| Pattern | Days | Seizures rise against | Why |
|---|---|---|---|
| C1 perimenstrual | −3 to +3 | Follicular and luteal days | Progesterone and allopregnanolone fall before menses |
| C2 periovulatory | 10 to −13 | Follicular and luteal days | The preovulatory estrogen surge, not yet opposed by progesterone |
| C3 luteal, in inadequate luteal-phase cycles | 10 to +3 | Follicular days (4 to 9) | Estrogen rises at midcycle but progesterone stays low |
Making the diagnosis. Ask for a diary of seizures and bleeding days over two or three cycles. A midluteal (day 22) progesterone below 5 ng/mL marks an inadequate luteal phase. The calculator applies Herzog's comparisons to one charted cycle.
Optimize the everyday ASM first. The options below all rest on small or uncontrolled studies. A Cochrane review found only four randomized trials that met its criteria (treatment for at least 12 weeks), all of progesterone or norethisterone (Maguire 2021).
| Option | Evidence |
|---|---|
| Clobazam around menses, 20–30 mg daily for about 10 days | Double-blind crossover in 18 women: clobazam preferred by 14 (Feely 1982). Needs predictable cycles; clobazam may make hormonal contraception less effective. |
| Acetazolamide, intermittent or daily | Retrospective survey of 20 women: 40% reported at least 50% fewer seizures (Lim 2001). |
| A temporary rise in the usual ASM dose over the vulnerable days | Common practice; not tested in trials. |
| Progesterone lozenges, 200 mg three times daily on days 14–25, then tapered over days 26–28 | NIH trial, 294 women: no benefit overall. Post hoc, women whose seizures at least tripled perimenstrually responded more often: 37.8% vs 11.1% on placebo (Herzog 2012). |
| Suppressing the cycle: depot medroxyprogesterone, continuous hormonal contraception, GnRH analogues | Uncontrolled series only; for example, of 14 women with uncontrolled seizures given medroxyprogesterone, the 11 analyzed had 30% fewer seizures a month (Mattson 1984). Consider interactions and bone health. |
An unplanned pregnancy carries more risk with epilepsy, which is on the CDC's list of such conditions, and a switch away from valproate or topiramate takes months to plan. Choose a method that the ASM does not weaken.
Convulsive seizures are the main danger to mother and baby, so the guideline's first priority is to minimize them (Level A). Death during the delivery hospitalization was 80 per 100,000 deliveries in women with epilepsy against 6 per 100,000 in women without, and preeclampsia, preterm labor and stillbirth were modestly more common (MacDonald 2015). In the UK, SUDEP caused 11 of 14 epilepsy-related maternal deaths in 2006–08 (Edey 2014).
| Risk Level | Medications | Notes |
|---|---|---|
| High Risk | Valproate; also phenobarbital and topiramate when clinically feasible alternatives exist | Valproate has a dose-dependent risk of major malformations (neural tube, cardiac) and lowers IQ and raises autism risk. The guideline says to avoid it when clinically feasible, to avoid phenobarbital (cardiac malformations) and phenobarbital and topiramate (oral clefts), and to avoid valproate and topiramate to reduce babies born small for gestational age. |
| Intermediate | Carbamazepine, Phenytoin | Risk varies by medication and dose; carbamazepine above 700 mg/day carried more than twice the odds of levetiracetam. Use the fewest medications and lowest effective doses compatible with seizure control. |
| Lowest Risk | Lamotrigine, Levetiracetam, Oxcarbazepine | The 2024 guideline says to consider these to minimize major congenital malformations (Level A). No medication is universally safest for every epilepsy. |
| ASM | Lower dose | Middle dose | Higher dose |
|---|---|---|---|
| Valproate | ≤650 mg: 6.3% | 651–1450 mg: 11.3% | >1450 mg: 25.2% |
| Phenobarbital | ≤80 mg: 2.7% | 81–130 mg: 6.2% | >130 mg: 11.7% |
| Carbamazepine | ≤700 mg: 4.5% | — | >700 mg: 7.2% |
| Lamotrigine | ≤325 mg: 2.5% | — | >325 mg: 4.3% |
Malformation rate by daily dose at conception, EURAP 2018. Dose dependence was significant for all four.
Clearance rises through pregnancy and falls back within weeks of delivery. In MONEAD, 23% of pregnant women had more seizures that impaired awareness, about the same as nonpregnant women with epilepsy (25%), but the pregnant women's doses were changed more than twice as often (74% vs 31%; Pennell 2020). Monitoring and adjusting doses is part of why.
Breastfeeding is encouraged. In NEAD, children who were breastfed had an IQ 4 points higher at age 6 than those who were not (Meador 2014). In MONEAD about half of infant blood levels were too low to measure; the median infant level was 28.9% of the mother's for lamotrigine and 5.3% for levetiracetam (Birnbaum 2020). Watch for sedation and poor feeding with phenobarbital, primidone and benzodiazepines.
Evidence is thin. The only cohort of people with a seizure history had 34 people: 21 on masculinizing and 13 on feminizing therapy. More had seizures only before starting hormones than only after (18 vs 6), and feminizing therapy made no significant difference (Blackman 2025). In a US inpatient database of 4,765 transgender women, feminizing hormones were not associated with seizures during hospitalization (Reddy 2026). Single case reports describe seizures increasing after estradiol was started. The rest is extrapolated from contraception and menopause data, so plan changes with the endocrinologist and follow the individual closely.
Seizures often worsen in perimenopause, when estrogen swings high relative to progesterone, especially in women with a catamenial pattern. After menopause the picture is mixed, and a past catamenial pattern predicted improvement (Harden 1999). Menopause came earlier in women with more seizures: at a mean 46.7 years with frequent seizures against 49.9 years with infrequent ones (Harden 2003).
Primary guidance: AAN/AES/SMFM practice guideline on teratogenesis, perinatal and neurodevelopmental outcomes after in-utero ASM exposure (Pack 2024); US Medical Eligibility Criteria for Contraceptive Use (CDC 2024); RCOG Green-top Guideline 68. This topic supports counseling and does not replace individualized neurology, obstetric, endocrine and maternal-fetal-medicine care.
Do not use this older table as a current counseling calculator. It reproduces selected results from 2006–2012 publications with different enrollment, comparator, dose, and outcome methods. Current counseling should use the 2024 AAN/AES/SMFM guideline and the latest pregnancy-registry publications. The historical data remain useful for illustrating dose dependence and why estimates differ among registries.
| Medication | NAAPR (Hernandez-Diaz 2012) | UK Register (Morrow 2006) | EURAP (Tomson 2011) |
|---|---|---|---|
| Lamotrigine | 2.0% | 3.2% | 2.0% (<300mg) 4.5% (≥300mg) |
| Levetiracetam | 2.4% | 0% (small sample) | - |
| Carbamazepine | 3.0% | 2.2% | 3.4% (<400mg) 8.7% (≥1000mg) |
| Phenytoin | 2.9% | 3.7% | - |
| Valproate | 9.3% | 6.2% | 5.6% (<700mg) 24.2% (≥1500mg) |
| Topiramate | 4.2% | 7.1% | - |
| Phenobarbital | 5.5% | - | 5.4% (<150mg) 13.7% (≥150mg) |
| Unexposed / Control | 1.1% | 3.5% | - |